Просмотр новости
Найдите то, что Вас интересует
 Спутники
 РН
 SpaceX
 Роскосмос
 NASA
СпутникиРНSpaceXРоскосмосNASAIn the fall of 1977, Rosie Jimenez, a 27-year-old single mother in McAllen, Texas, needed an abortion. Just months earlier Medicaid would have covered the procedure. But the Hyde Amendment, a new rule banning Medicaid coverage for abortion, had just taken effect. Unable to afford the more than $200 cost of an abortion from a licensed clinician, she turned to a midwife who was technically unlicensed to preform abortions.
Jimenez died from that unsafe procedure. She is widely known as the first documented death from the Hyde Amendment.
Fifty years later, countless women across the U.S. have had their lives forever changed by this archaic, racist, sexist and classist amendment.
The post Abortion Belongs in Pregnancy Care—And Your Insurance Should Cover It appeared first on Ms. Magazine.
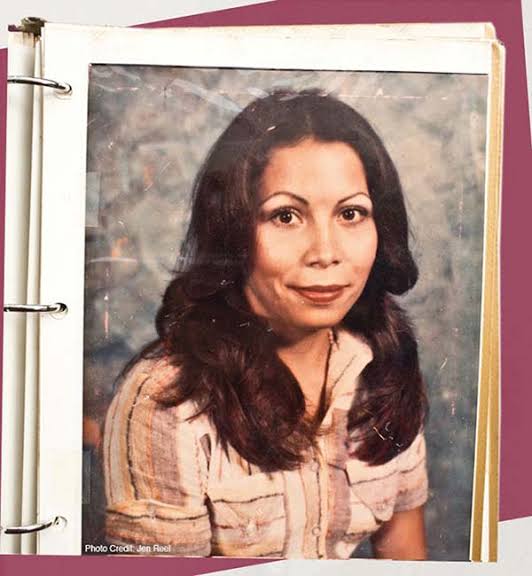 Rosie Jimenez died in 1978 following an illegal abortion after the passage of the Hyde Amendment, which banned public funding for the procedure. (Jen Reel via Texas Observer)
In the fall of 1977, Rosie Jimenez, a 27-year-old single mother in McAllen, Texas, needed an abortion. Just months earlier Medicaid would have covered the procedure. But the Hyde Amendment, a new rule banning Medicaid coverage for abortion, had just taken effect. Unable to afford the more than $200 cost of an abortion from a licensed clinician, she turned to a midwife who was technically unlicensed to preform abortions.
Jimenez died from that unsafe procedure. She is widely known as the first documented death from the Hyde Amendment.
Fifty years later, countless women across the U.S. have had their lives forever changed by this archaic, racist, sexist and classist amendment.
 An abortion-rights demonstration at Boston City Hall Plaza on Oct. 3, 1991, to commemorate the death of Rosie Jimenez. (Justine Ellement / The Boston Globe via Getty Images)What Is the Hyde Amendment?
First attached to a federal spending bill in 1976, Hyde withholds abortion coverage from people enrolled in Medicaid except in the narrowest circumstances. It was created by Henry Hyde, a staunch anti-abortion congressman who, because he couldn’t ban abortion outright, used the full weight of the federal government to put abortion care out of reach for low-income families. Over the years, similar restrictions have expanded to federal employees and their families, military service members, Native people who rely on the Indian Health Service, Peace Corps volunteers, people in federal prisons and immigration detention and low-income residents of the District of Columbia. Hyde is not permanent law. Congress chooses to include it, year after year.
Half a Century of Hyde’s ConsequencesThis 50th year should not be an anniversary we simply mark. It should be a reckoning with 50 years of harm and how to fix it.
For much of the U.S.’s early history, abortion was not set apart from pregnancy care. Midwives cared for people through pregnancy, birth, miscarriage, abortion and the postpartum period, and abortion before quickening was generally legal. That began to change in the nineteenth century, when the newly organized medical profession pushed to criminalize abortion and displace midwives. Even in 1900, midwives attended roughly half of all U.S. births and in the South, Black midwives attended as many as three in four well into the twentieth century. But licensing systems steadily pushed Black, immigrant and community midwives out of practice. Care was broken apart: obstetrics moved into hospitals, miscarriage care into emergency rooms and, after Roe, abortion into freestanding clinics.
How Hyde Deepened the Divide in Reproductive HealthcareBefore Hyde took effect, Medicaid covered abortion as part of health care. Afterward, people with low incomes could use their insurance for prenatal visits, labor and delivery and miscarriage management, but not for an abortion. The government did not eliminate the need for abortion. It simply sent the bill to the people least able to pay it.
Today, Medicaid is the backbone of pregnancy care in the U.S. It finances about 41 percent of births nationwide and more than half of births in Louisiana, Mississippi, New Mexico and Oklahoma. It covers prenatal care, childbirth, miscarriage management and, in most states, a full year of care after delivery. But because of Hyde, it generally will not cover abortion, even when the medications and procedures are the same ones clinicians use to treat other pregnancy loss.
For a family living paycheck to paycheck, that distinction is devastatingly concrete. Recent national median self-pay charges were $563 for medication abortion, $650 for a first-trimester procedure and $1,000 for a second-trimester procedure. For a family of three at the federal poverty line, that can consume a quarter to nearly half of a month’s income, before travel, lodging, child care, or lost wages. Since Dobbs, those added costs have only grown.
Research shows that when Medicaid does not cover abortion, one in four women seeking one are forced to continue the pregnancy because they cannot afford the procedure. Others lose precious time raising money, making their care more expensive and harder to obtain.
And Hyde’s burden is not shared equally.
About 7.8 million women of reproductive age are enrolled in Medicaid in states that do not use their own funds to cover abortion and half are women of color. Black and Latina women are more likely than white women to be enrolled in Medicaid and already face profound inequities in maternal health. Rural families face hospital closures and maternity care deserts. Hyde takes every existing inequity and doubles down on it.
The damage also reaches beyond people who seek abortions. Since Dobbs, we have watched patients experiencing miscarriages and dangerous pregnancy complications wait while clinicians, lawyers and hospital administrators decide whether treatment could expose someone to prosecution. That confusion is not accidental. It is the predictable result of pretending abortion can be carved away from pregnancy care without affecting everything around it.
So what do we do? The answer is almost a little too simple. We need to integrate abortion back into the full spectrum of pregnancy care and strengthen the system responsible for delivering it.
That begins with ending the Hyde Amendment and related coverage bans by passing the EACH Act, so that a person’s insurance works regardless of how a pregnancy ends. But coverage on paper will mean little if Medicaid is too underfunded to sustain the hospitals, clinics, midwives, doulas and community health workers people depend on. Medicaid reimbursement must reflect the actual cost of high-quality pregnancy care. Congress must also protect continuous postpartum coverage, reverse cuts that push millions off insurance and stop excluding trusted reproductive health providers from the program.
This is not only an abortion policy agenda. It is a maternal health agenda, a rural health agenda, an economic justice agenda and a racial justice agenda. The health system cannot support people through birth while abandoning them during miscarriage. It cannot celebrate motherhood while forcing mothers to sacrifice rent, food, or their own health to obtain care.
Hyde helped teach our health system to treat abortion as morally suspect, clinically separate and financially optional. After fifty years, that separation can feel normal. It is not. It was constructed through policy and policy can dismantle it.
I often say that we need to talk about where we want to go as much as what we don’t like. So on this anniversary, let us hold the harm of Hyde while boldly proclaiming that 50 years is too long. It’s time for a new vision, one where insurance follows the patient regardless of the outcome and honors our full freedom over our bodies.
*
A note from Ms. editors: We want to hear from you for The Majority, a new campaign collecting stories about how reproductive freedom has enabled readers to build the lives they want and need.

Poll after poll shows a majority of Americans support reproductive healthcare access. Yet public debate overlooks the lives shaped by abortion access, contraception, IVF, miscarriage care, maternal healthcare or comprehensive sex education—countless women who chose to pursue an education, have children, not have children, protect their health and chart their own future. What’s your reproductive freedom story? Add your voice. Together, these stories will help show not only why reproductive freedom remains a majority value, but also what it makes possible.